
Showing posts sorted by relevance for query blood. Sort by date Show all posts
Showing posts sorted by relevance for query blood. Sort by date Show all posts
Friday, April 27, 2018
Simple blood tests that tells us where we are with our melanoma....AGAIN (and again, and again, and again)!!!
I have been yelling about simple blood tests that give good information to melanoma patients for YEARS!! I think my first post was in 2015. Here is some of what I said and a link to that February post (with a zillion links within): "Yep. It's me again, Margaret. I'm still yelling about simple blood draws that can provide critical information related to the diagnosis of, feasibility of treatment for, response to treatment, and prognosis generally in melanoma patients!" Simple blood tests that tell us how melanoma patients are responding to therapy and identify their disease in the first place....AGAIN!!!!
On a rather disheartening note ~ At a recent symposium for melanoma patients in Atlanta, facilitated by Northside and MRF, with "melanoma specialists" from Emory and Northside Hospital, I asked the panel what they were utilizing in regard to blood assays in diagnosing, monitoring, and implementing treatment for their patients. They looked at me like deer in the headlights!! One blathered on about it only being useful in regard to diagnosing BRAF status, not being "validated", blah, blah, blah. Seriously??? I call - B.S.!!!! Some of these tests are not particularly special, like the NLR (neutrophil-to-lymphocyte ratio) for instance. This is easily attained and computed via a simple CBC (complete blood count) drawn at every lab in this country a zillion times a day. AND...we have looked at this data long enough to know that it is true!!!
Okay. I'll quit yelling. Now, there's this ~
Neutrophil-to-lymphocyte Ratio (NLR) as a predictor for recurrence in patients with stage III melanoma. Ma, Kuzman, Ray, et al. Sci Rep. 2018 Mar 6.
Neutrophil-to-lymphocyte ratio is a strong predictor for overall survival and disease free survival in many cancers. Our study is the first investigation aiming to determine the predictive value of neutrophil-to-lymphocyte ratio on prognosis of patients with stage III melanoma. This retrospective study utilized a cohort of 107 patients with stage III melanoma treated at Huntsman Cancer Institute, University of Utah, from May 2002 to March 2016. The optimal cutoff of neutrophil-to-lymphocyte ratio was determined by the significance of log-rank tests. A total of 97 log-rank tests were conducted to find the optimal cutoff. Disease free survival was assessed using the Kaplan-Meier method, and univariable and multivariable Cox models were applied to evaluate the predictive value of neutrophil-to-lymphocyte ratio. 2.5 was identified as the optimal cutoff. Kaplan-Meier curve showed that the disease free survival rate of the low value group was significantly higher compared to that of high value group. After adjusting for confounders and other prognostic factors, the neutrophil-to-lymphocyte ratio greater than or = to 2.5 remained a strong predictor for disease recurrence in patients with stage III melanoma.
Liquid biopsy to monitor melanoma patients. Gaiser, von Bunoff, Gebhardt, Utikal. J Dtsch Dermatol Ges. 2018 Mar 7.
During the last six years, several innovative, systemic therapies for the treatment of metastatic malignant melanoma (MM) have emerged. Conventional chemotherapy has been superseded by novel first-line therapies, including systemic immunotherapies (anti-CTLA4 and anti-PD1; authorization of anti-PDL1 is anticipated) and therapies targeting specific mutations (BRAF, NRAS, and c-KIT). Thus, treating physicians are confronted with new challenges, such as stratifying patients for appropriate treatments and monitoring long-term responders for progression. Consequently, reliable methods for monitoring disease progression or treatment resistance are necessary. Localized and advanced cancers may generate circulating tumor cells and circulating tumor DNA (ctDNA) that can be detected and quantified from peripheral blood samples (liquid biopsy). For melanoma patients, liquid biopsy results may be useful as novel predictive biomarkers to guide therapeutic decisions, particularly in the context of mutation-based targeted therapies. The challenges of using liquid biopsy include strict criteria for the phenotypic nature of circulating MM cells or their fragments and the instability of ctDNA in blood. The limitations of liquid biopsy in routine diagnostic testing are discussed in this review.
Liquid Profiling of Circulating Tumor DNA in Plasma of Melanoma Patients for Companion Diagnostics and Monitoring of BRAF Inhibitor Therapy. Haselmann, Gebhardt, Brechtel, et al.Clin Chem. 2018 Feb 26.
The current standard for determining eligibility of patients with metastatic melanoma for BRAF-targeted therapy is tissue-based testing of BRAF mutations. As patients are rarely rebiopsied, detection in blood might be advantageous by enabling a comprehensive assessment of tumor mutational status in real time and thereby representing a noninvasive biomarker for monitoring BRAF therapy.
In all, 634 stage I to IV melanoma patients were enrolled at 2 centers, and 1406 plasma samples were prospectively collected. Patients were assigned to 3 separate study cohorts: study 1 for assessment of circulating tumor DNA (ctDNA) as part of companion diagnostics, study 2 for assessment of ctDNA for patients with low tumor burden and for follow-up, and study 3 for monitoring of resistance to BRAF inhibitor (BRAFi) or mitogen-activated protein kinase inhibitor therapy.
Overall, a high degree of concordance between plasma and tissue testing results was observed at 90.9% (study 1) and 90.1% (study 2), respectively. Interestingly, discrepant results were in some cases associated with nonresponse to BRAFi (n = 3) or a secondary BRAF-mutant malignancy (n = 5). Importantly, ctDNA results correlated with the clinical course of disease in 95.7% and with response to treatment. Significantly, the detection of BRAF mutant ctDNA preceded relapse assessed by Response Evaluation Criteria in Solid Tumors, and was more specific than serum S100 and lactate dehydrogenase.
Blood-based testing compares favorably with standard-of-care tissue-based BRAF mutation testing. Importantly, blood-based BRAF testing correlates with the clinical course, even for early-stage patients, and may be used to predict response to treatment, recurrence, and resistance before radioimaging under BRAFi therapy, thereby enabling considerable improvements in patient treatment.
Early evolution of BRAFV600 status in the blood of melanoma patients correlates with clinical outcome and identifies patients refractory to therapy. Gonzalez-Cao, Mayo de Las Casas, Jordana, et al. Melanoma Res. 2018 Feb 23.
Serial analysis of BRAF mutations in circulating-free DNA (cfDNA) could be of prognostic value in melanoma patients. We collected blood samples from 63 advanced BRAFV600E/K melanoma patients and determined BRAFV600E/K status in cfDNA using a quantitative 5'-nuclease PCR-based assay. Levels of BRAF mutation in pre-cfDNAs were associated significantly with tumour burden, progression-free survival and overall survival. Changes in BRAF status in cfDNA after initiation of treatment (early-cfDNA) had a significant correlation with outcome. In patients with persistent BRAF mutations (n=12), progression-free survival and overall survival were 3.5 months and 5.3 months compared with 16.6 months and 21.9 months in patients with BRAF negativization (n=16), and 15.1 months and NR in patients who maintained their initial negative status (n=12). The median duration of response in patients with radiological response, but persistence of BRAFV600 in early-cfDNA (n=5) was 4 months. Our study indicates that serial BRAF testing in the blood of advanced melanoma identifies patients refractory to therapy.
And these are just a handful of reports!!! They don't even address other blood assays of which we know a great deal, including CD4+ T cells, microRNA, gene expressions, and circulating melanoma cells. I am just one little woman sitting in Chattanooga, TN!! With melanoma. Without a salary for this effort. But with a computer and basic common sense! You "melanoma experts" need to do better!!! Get with the program. These tests are available, have important implications for melanoma patients, and we need YOU to get on board and start incorporating them in your management of melanoma patients NOW! Some folks don't have the luxury of waiting around for you to get off your hands! Liquid blood assays WILL be utilized to diagnosis, monitor and evaluate melanoma patients for appropriate treatment choices!! They are not likely to be the sole, end-all-be-all answer to all things melanoma, but will certainly be an essential component of basic care. We need you peeps to make it so...SOONER...rather than later. C'mon, man!!!! (It's good that ratties have long tails! We need them!) - c


Thursday, March 14, 2019
Circulating tumor DNA (ctDNA) as a way to predict survival in Stage III melanoma patients
If you have Stage III melanoma, trying to determine whether or not to embark on adjuvant treatment (treatment taken after all obvious melanoma has been removed) via either immunotherapy or targeted therapy is - at best - difficult!!! Will such treatment really help? Well, the data strongly supports - YES!!! Here are a zillion such articles! But, we also know that some folks can remain Stage III for years and years with no advancement of their disease. Is the very real possibility of significant life changing side effects worth it? Wouldn't it be great if you could do a simple blood test to see if you fall among the folks who are Stage III AND at increased risk for progression if you do not attain treatment?
Well! Before we get to that, remember all my rants about simple blood tests that can tell us soooooooo much about our melanoma status? Here are a few zillion of those - looking at circulating tumor DNA (little bits of tumor, floating around in our blood) in particular: The many ways measuring circulating tumor DNA can help melanoma patients Basically, that link takes you to tons and tons of data, with some of my explanations, about what measuring circulating bits of tumor via a simple blood draw can do to impact melanoma patients and their treatment choices. I note: "There are many blood markers, all much easier to collect that actual tumor samples, that can be used to diagnosis melanoma, determine tumor type, prognosis and response to therapy."
Here's the latest:
Pre-operative ctDNA predicts survival in high-risk stage III cutaneous melanoma patients. Lee, Saw, Thompson, et al. Ann Oncol. 2019 Mar 12.
The outcomes of patients with stage III cutaneous melanoma who undergo complete surgical resection can be highly variable, and estimation of individual risk of disease relapse and mortality remains imprecise. With recent demonstrations of effective adjuvant targeted and immune checkpoint inhibitor therapy, more precise stratification of patients for costly and potentially toxic adjuvant therapy is needed. We report the utility of pre-operative circulating tumour DNA (ctDNA) in patients with high-risk stage III melanoma.
ctDNA was analysed in blood specimens that were collected pre-operatively from 174 patients with stage III melanoma undergoing complete lymph node dissection. Cox regression analyses were used to evaluate the prognostic significance of ctDNA for distant metastasis recurrence free survival (DM-RFS) and melanoma specific survival (MSS).
The detection of ctDNA in the discovery and validation cohort was 34% and 33% respectively, and was associated with larger nodal melanoma deposit, higher number of melanoma involved LNs, more advanced stage and high lactose dehydrogenase (LDH) levels. Detectable ctDNA was significantly associated with worse MSS in the discovery and validation cohort and remained significant in a multivariable analysis. ctDNA further sub-stratified patients with AJCC stage III substage, with increasing significance observed in more advanced stage melanoma.
Pre-operative ctDNA predicts MSS in high-risk stage III melanoma patients undergoing complete LN dissection, independent of stage III subclass. This biomarker may have an important role in prognosis and stratifying patients for adjuvant treatment.
So ~ in this study researchers looked at one group of Stage III melanoma patients to see how many of them would have circulating tumor DNA present in their blood sample. Then they took another group to determine the presence of ctDNA and its correlation to other risk factors and melanoma outcomes. They determined that the presence of circulating bits of tumor in the blood was consistent across both groups at about 34%. They found that ctDNA in the Stage III melanoma patient's blood was associated with those who had larger amounts of tumor in melanoma positive lymph nodes, a greater number of lymph nodes affected, advanced stage, and increased LDH levels. In the end, when they looked at all the variables, ctDNA was significantly associated with melanoma specific survival.
Is the presence of ctDNA the end all, be all? Of course not! BUT!!! If you knew where you stood in regard to bits of tumor floating in your blood - or NOT!! - then that could be critical in making a decision about whether or not to proceed with adjuvant treatment. Further, if I were a Stage IIIb patient today, as I was back in 2003, and found I did NOT have measurable ctDNA, I might be comfortable in postponing adjuvant treatment. HOWEVER, I would request serial blood draws to determine if that status changed over time, with the understanding that should ctDNA show up in my blood I would begin adjuvant therapy ASAP! I believe (given all the data I've reviewed) that evaluating patients for ctDNA is a much more sensitive and sensible way to follow Stage III peeps for progression than repeated radiographic scans and (hopefully!!!) will be the wave of the future.
So...what are we waiting for??????????? Lives are at stake! Let's make measuring ctDNA a routine, accepted method of evaluating melanoma patients - TODAY!!!! ~ c
Friday, June 23, 2017
ASCO 2017: Circulating DNA to measure response in melanoma
Wouldn't it be great if we could do a simple lab draw to determine the type of tumor, as well as tumor burden a patient has?? With such a test we could minimize use of painful biopsies, decrease repeated exposure to radiation via scans, and could much more rapidly determine whether a patient's tumor burden is decreasing in a positive response to a given therapy....or not!
I've been posting studies addressing these possibilities for a while...
From 2014: With immunotherapy tumors can grow or reappear...even though it is working. Will DNA analysis clarify response???
From 2015: PCR testing for melanoma
PCR testing for circulating melanoma DNA....one mo one!!
Circulating Tumor Cells...how they may eventually impact melanoma diagnosis and response to therapy
From 2016: Here, I actually broke down all the various biomarkers, what they are and what they mean ~ Biomarkers - blood components, circulating tumor cells AND of the tumor itself
Then there were these: BRAF testing via blood rather than tumor tissue
Blood tests to diagnose, check response to therapy, and use as follow-up in melanoma!
From 2017: Circulating DNA predicts response to anti-PD-1
Circulating tumor DNA provide valid way to monitor response to anti-PD-1 therapy for melanoma....AGAIN!!!
Now...there's this:
Circulating
tumor DNA as a predictor for response to treatment in BRAF V600E
mutant malignant melanoma.
ASCO
2017. J Clin Oncol 35, 2017. Braune, Buboff, Follo, et
al.
Background: Available biomarkers LDH and S100B possess limited sensitivity and specificity to predict outcome in melanoma. In this pilot study we evaluated the use of circulating tumor (ct)DNA harboring BRAF and NRAS mutations as a predictive biomarker for treatment response and progression-free survival (PFS) in patients with locally advanced or metastatic melanoma. Methods: We analyzed 89 retrospective plasma samples from 32 unselected pts, and 158 samples from 12 pts included in a prospective trial (DRKS00009507). We included stage III disease with planned resection or stage IV disease before initiation or change of medical treatment. Blood samples were taken at baseline at d +8, d +28, and thereafter at 3 months intervals for up to two years. We developed a hydrolysis probe based, Locked Nucleic Acid assay to detect BRAF V600E and wild type ctDNA by droplet digital PCR. Results were correlated with LDH, S100B and PFS. Results: Sensitivity of BRAF V600E specific assay was 0.01% with a limit of Blank of 0.28 copies/well. Of 31 stage IV pts with retrospective samples, 23 were positive for BRAF V600E ctDNA at least once (74%). Positive pts had a mean of 9 (range: 1-17) and 483 (range: 0.1-16,388) BRAF V600E copies/mL for stage III and stage IV respectively. The presence of ctDNA at baseline predicted poor PFS. A negative slope in BRAF V600E ctDNA was a favorable prognostic factor for PFS with a median PFS of 3.42 vs. 2.56 months (Range 1.87-8.9 vs. 0.89-5.02). Residual ctDNA at the first time point after initiation or change of treatment was related to a shorter PFS. Based on 144 measurement pairs, BRAF ctDNA strongly correlated with S100 and LDH. Conclusions: Residual ctDNA early after change or institution of treatment predicted tumor progression at first clinical response assessment. A positive to negative conversion or a decrease indicated a more favorable course. These data support the use of ctDNA as an early predictive marker for treatment response. We will examine whether two or more detected mutations indicate clonal heterogeneity and confer adverse prognosis.
Background: Available biomarkers LDH and S100B possess limited sensitivity and specificity to predict outcome in melanoma. In this pilot study we evaluated the use of circulating tumor (ct)DNA harboring BRAF and NRAS mutations as a predictive biomarker for treatment response and progression-free survival (PFS) in patients with locally advanced or metastatic melanoma. Methods: We analyzed 89 retrospective plasma samples from 32 unselected pts, and 158 samples from 12 pts included in a prospective trial (DRKS00009507). We included stage III disease with planned resection or stage IV disease before initiation or change of medical treatment. Blood samples were taken at baseline at d +8, d +28, and thereafter at 3 months intervals for up to two years. We developed a hydrolysis probe based, Locked Nucleic Acid assay to detect BRAF V600E and wild type ctDNA by droplet digital PCR. Results were correlated with LDH, S100B and PFS. Results: Sensitivity of BRAF V600E specific assay was 0.01% with a limit of Blank of 0.28 copies/well. Of 31 stage IV pts with retrospective samples, 23 were positive for BRAF V600E ctDNA at least once (74%). Positive pts had a mean of 9 (range: 1-17) and 483 (range: 0.1-16,388) BRAF V600E copies/mL for stage III and stage IV respectively. The presence of ctDNA at baseline predicted poor PFS. A negative slope in BRAF V600E ctDNA was a favorable prognostic factor for PFS with a median PFS of 3.42 vs. 2.56 months (Range 1.87-8.9 vs. 0.89-5.02). Residual ctDNA at the first time point after initiation or change of treatment was related to a shorter PFS. Based on 144 measurement pairs, BRAF ctDNA strongly correlated with S100 and LDH. Conclusions: Residual ctDNA early after change or institution of treatment predicted tumor progression at first clinical response assessment. A positive to negative conversion or a decrease indicated a more favorable course. These data support the use of ctDNA as an early predictive marker for treatment response. We will examine whether two or more detected mutations indicate clonal heterogeneity and confer adverse prognosis.
Makes sense, right? If you have a lot of circulating tumor DNA in your blood...that's not good. If you still have ctDNA floating around after you have started a new treatment...it doesn't bode well for you to respond well to that treatment. However, if you have little ctDNA period, or if the amount you have is decreasing with your treatment...it is likely that you will do well!!! Think how much more quickly we could get a patient on the treatment that works for them with a tool like this!!! I think we've beat around this bush for long enough!!! Let's make peripheral blood sample testing for circulating tumor DNA a reality!! - c
Saturday, June 6, 2015
Lab values that may predict response to Ipi/Yervoy????
This article is not from ASCO, but I thought it was interesting after my last post on eosinophilia being associated with a response to anti-PD1...
Baseline neutrophil-to-lymphocyte ratio is associated with outcome of ipilimumab-treated metastatic melanoma patients. Br J Cancer, 2015, May 26. Ferrucci, Gandini, Battaglia, et al.
Ipi improves survival of metastatic melanoma patients. Despite documented, durable objective responses, a significant number of patients fail to benefit. Patients treated at 3 Italian institutions - 187 dosed with 3 mg/kg ipi and 27 with 10mg/kg ipi - were evaluated. Neutrophil-to-lymphocyte ratio (NLR) was calculated from pre-therapy blood counts. In the training cohort of 69 patients, pre-therapy NLR was identified as the strongest and independent marker for treatment benefit in multivariate analyses. Patients with baseline NLR less than 5, had a significantly improved progression free survival and overall survival compared to those with a NLR equal or greater than 5. Associations of low NLR with improved survival were confirmed in three validation cohorts.
Background info:
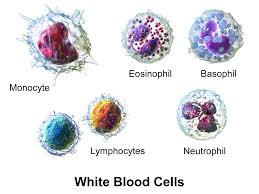
Neutrophils are the most frequent kind of white blood cell (40-75%) we have. They form from stem cells in the bone marrow. They live only 5-90 hours. They can undergo chemotaxis, which allows them to travel rapidly to the site of an infection or inflammation. Once there, they release cytokines that increase the inflammatory process and attracts other cells to the area. They can ingest microorganisms or particles, thereby helping fight off disease. Low neutrophils = neutropenia, can happen in anemia, in some types of leukemia, or be caused by medicines like chemo....leaving the person at risk for infection.
Lymphocytes are any of 3 types of white blood cell: natural killer cells, T cells or B cells, all of which play a role in immunity. They are the main cell found in lymph, ergo the name. They live for weeks to years to a lifetime (a good thing when thinking about immunity!!), much longer than other white cells. NK cells generally kill viruses and tumor cells. Helper T cells release cytokines and growth factors that regulate other immune cells. Cytotoxic T cells also kill cells infected with viruses and tumor cells. B cells work in the secretion of antibodies. Increased levels of lymphocytes - lymphocytosis - is often a sign of a viral infection. Increased lymphs in the presence of decreased numbers of neutrophils can be due to lymphoma. Decreased lymphocytes - lymphocytopenia - is usually due to infection (like HIV), surgery or trauma and leaves the person immunocompromised.
A simple test from a basic blood collection is a CBC, which is a complete blood count. It tells you the number of red blood cells, white blood cells, hemoglobin, hematocrit, sizes of various cells, and the number of platelets in your blood. A differential is usually run with the CBC and it breaks down the number of all the white blood cells. Normal counts of the various white blood cells are broken down in percentages:
- Neutrophils: 40% to 60%
- Lymphocytes: 20% to 40%
- Monocytes: 2% to 8%
- Eosinophils: 1% to 4%
- Basophils: 0.5% to 1%
- Bands (young neutrophils): 0% to 3%
Monday, February 26, 2018
Simple blood tests that tell us how melanoma patients are responding to therapy and identify their disease in the first place....AGAIN!!!!
Yep. It's me again, Margaret. I'm still yelling about simple blood draws that can provide critical information related to the diagnosis of, feasibility of treatment for, response to treatment, and prognosis generally in melanoma patients! Just last week I posted this: More blood tests to determine prognosis as well as response to therapy in melanoma patients!!!
Now, there's this....
Clinical response to PD-1 blockade correlates with a sub-fraction of peripheral central memory CD4+ T cells in patients with malignant melanoma. Takeuchi, Tanemura, Tada, et al. Int Immunol. 2017 Dec 23.
Cancer immunotherapy that blocks
immune checkpoint molecules, such as PD-1/PD-L1, unleashes
dysfunctional antitumor T-cell responses and has durable clinical
benefits in various types of cancers. Yet its clinical efficacy is
limited to a small proportion of patients, highlighting the need for
identifying biomarkers that can predict the clinical response by
exploring antitumor responses crucial for tumor regression. Here we
explored T-cell responses associated with clinical benefits using
peripheral blood mononuclear cells (PBMCs) from patients with
malignant melanoma treated with anti-PD-1 monoclonal antibody (mAb).
Pre- and post-treatment samples were collected from two different
cohorts (discovery set and validation set) and subjected to mass
cytometry assays that measured the expression levels of 35 proteins.
Screening by high dimensional clustering in the discovery set
identified increases in three micro-clusters of CD4+ T cells, a
subset of central memory CD4+ T cells harboring CD27+FAS-CD45RA-CCR7+
phenotype, after treatment in long-term survivors, but not in
non-responders. The same increase was also observed in clinical
responders in the validation set. We propose that increases in this
subset of central memory CD4+ T cells in peripheral blood can be
potentially used as a predictor of clinical response to PD-1 blockade
therapy in patients with malignant melanoma.
Here researchers looked at the blood of folks before and after patients with melanoma were treated with anti-PD-1. They found that a particular type of CD4+ T cell increased in long term survivors and clinical responders...but NOT in non-responders.That seems pretty straight forward to me! But, there's more....
A high neutrophil to lymphocyte ratio prior to BRAF inhibitor treatment is a predictor of poor progression-free survival in patients with metastatic melanoma. Finon, Zaragoza, Maillard, et al. Eur J Dermatol. 2018 Jan 16.
Some studies have shown that a high neutrophil/lymphocyte ratio (NLR) greater than or = to 4 before initiating ipilimumab treatment is an independent prognostic indicator of poor survival in patients with metastatic melanoma (MM). To determine whether the NLR before starting BRAF inhibitor (BRAFi) treatment in patients with (MM) is associated with progression-free survival (PFS). This retrospective study included 49 patients consecutively receiving BRAFi for MM between July 2012 and December 2014. Cox proportional hazards regression was used to analyse the relationship between NLR and other factors, such as lactate dehydrogenase (LDH), performance status, BRAFi as first- or second-line therapy, and corticosteroid intake with PFS. The NLR before starting BRAFi was significantly associated with PFS based on univariate analysis and multivariate analysis adjusted for potential confounding factors, such as LDH activity, ulceration, performance status, first-line therapy, and corticosteroid intake. A high NLR (continuous variable) was associated with short PFS, and NLR greater than or = to 4 was associated with shorter PFS . Corticosteroid intake was not associated with short PFS based on multivariate analysis. An NLR greater than 4, before starting BRAFi treatment, is an independent prognostic indicator of poor progression-free survival.
SO.....again ~ folks with a high NLR (greater than or = to 4) did worse!!! This is NOT news people. I've been yelling about this since 2015!!!
That fact was valid when the NLR was tested in folks without metastatic disease ~ Neutrophil-to-lymphocyte ratios as a predictor of death from melanoma in patients with NONmetastatic disease
That fact was valid when the NLR was examined in regard to ipi (as noted in the above article) ~ Neutrophils as a prognostic predictor in patients trated with ipi/Yervoy
That fact was valid when first postulated in 2015 ~ Lab values that may predict response to Ipi/Yervoy????
Do we really need to examine that any further??? There is also this...
Development and validation of a plasma-based melanoma biomarker suitable for clinical use. Van, Lincoln, Van Laar. Br J Cancer. 2018 Jan 23.
In
Australia, more money is spent on skin cancer than any other
malignancy. Despite this, the mortality rate of melanoma, the
deadliest form, has steadily increased over the past 50 years.
Diagnostic imprecision and a lack of complimentary molecular
biomarkers are partially responsible for this lack of progress.
Whole-microRNAome
profiling was performed on plasma samples from 32 patients with
histologically confirmed melanoma and 16 normal controls. A
classification algorithm was trained on these data and independently
validated on multiple previously published microRNA data sets,
representing (i) melanoma patient- and normal-blood, (ii) melanoma
and nevi biopsy tissue, and (iii) cell lines and purified exosomes.
38
circulating microRNAs had biologically and statistically significant
differences between melanoma and normal plasma samples (MEL38). A
support vector machine algorithm, trained on these markers, showed
strong independent classification accuracy (AUC 0.79-0.94). A
majority of MEL38 genes have been previously associated with melanoma
and are known regulators of angiogenesis, metastasis, tumour
suppression, and treatment resistance.
MEL38
exhibits disease state specificity and robustness to platform and
specimen-type variation. It has potential to become an objective
diagnostic biomarker and improve the precision and accuracy of
melanoma detection and monitoring.
Here folks looked at blood samples for microRNA whose presence helped define the difference between melanoma and normal plasma.
I have endless posts regarding the examination of tumor DNA in the blood of melanoma patients, allowing for the identification of disease, BRAF status, progression, response, etc. Earlier this month, I posted this: Circulating tumor DNA to help differentiate true progression of melanoma vs pseudoprogression in patients treated with anti-PD-1 Here are about a zillion additional posts: Circulating melanoma DNA
Really people! Can someone not do a definitive study on a larger scale...rather than piecemeal this and that....without sharing data...to come up with a valid and specific melanoma panel??? We have simple lipid panels that help guide heart health. We have lab draws and tests that help diagnosis and monitor diabetes. No set of labs is an absolute for ANYTHING. BUT!!!! They are incredibly important tools in diagnosing, treating and managing a wide variety of disease processes. They can do that for melanoma, too!!! We have learned that we can look at T cells, other basic blood cells, tumor DNA, RNA, all sorts of bits and bobs....floating in the blood of patients with melanoma, to provide meaningful information that could allow melanoma patients and their doctors a mechanism for making better choices in their treatment and care.
Radiologic scans expose us to radiation, "find" lots of red herrings, and are a huge financial burden. They also have limits regarding what they can see. Sub-centimeter tumors, not to mention little demon melanoma cells floating about, are not visualized. Additionally, imaging studies are cumbersome and have a built in time lag that can delay needed therapy or a change in current therapy as patients wait for "their next scan" to be compared to a prior one in order to define disease status. Determining pathology from tumor samples is often confusing. I had to have my initial slides examined by 3 pathologists to gain consensus that I was in fact dealing with melanoma. Folks need and deserve answers. A basic algorithim that incorporates all forms of investigation including blood markers, nuclear, radiographic, and tissue examination needs to be established for melanoma. NOW!!!
Seriously..NOW!!! - c
Friday, December 15, 2017
Another look at a recent study of proteins in our blood that predict response to anti-PD-1!!!
A couple of days ago I posted this: A simple blood draw to measure serum protein - predicts outcome for melanoma patients treated with anti-PD-1????
It is a review of the article you can find here and peruse yourself: A Serum Protein Signature Associated with Outcome After Anti-PD1 Therapy in Metastatic Melanoma Jeffrey S. Weber, Mario Sznol, Ryan J. Sullivan, Shauna Blackmon, Genevieve Boland, Harriet M Kluger, Ruth Halaban, Antonella Bacchiocchi, Paolo A Ascierto, Marilena Capone, Carlos Oliveira, Krista Meyer, Julia Grigorieva, Senait G Asmellash, Joanna Roder and Heinrich Roder Cancer Immunol Res December 8 2017
Some of my peeps had a few more questions, and I found the whole shmegegge super interesting, (Especially when you think about it in light of all the other potential that a simple blood analysis has regarding tumor burden and other biomarkers: Measuring cell-free DNA in melanoma patient's blood to determine tumor burden and prognosis!) so here is a more thoughtful analysis than my first.....
After a thorough review of the entire
article, along with all the tables and figures with my trusty
B....here's what we got:
Dr. Weber made an earlier presentation
of some of this data at a conference in 2015...so it's been cooking a
while.
The main gist is pretty straight
forward: Researchers used pooled data from multiple institutions and several
studies of ratties (n = 289) who took nivo, pembro, ipi, or the
ipi/nivo combo (along with those of us who took nivo with peptide
vaccines). Some of the ratties had already had ipi, before taking
anti-PD-1 and some had not. Blood was drawn before the ratties
started treatment. Those samples were analyzed using advanced
techniques to tease out what proteins in the blood were present in
the sensitive set (patients who responded) vs the resistant set
(patients who did not). After that first examination was completed,
researchers used the same protein markers on test sets. The protein
markers were successful in distinguishing those likely to be
sensitive (responders) from those who were likely to be resistant
(non-responders). In addition, they analyzed the proteins to
identify the mechanisms of sensitivity or resistance. There they
found proteins associated with:
1. wound healing
2. active phase
reactants (the body's inflammatory response)
3. complement activation
(another immune mechanism we use to respond to abnormal molecules –
which could be anything from worms to cancer).
This test clearly worked to predict
response for folks taking anti-PD-1 alone or taking ipi alone.
However, when ipi/nivo was taken together the proteins were not
predictive of response. (As an aside if you look at the
graphs...Sets 2 and 3 are not currently significant, probably because
the length of time passed at review of data was not adequate.) You can take a look at the graphs in the link above or my pic below.

Researchers repeatedly note that
application of this test to a larger group is needed to validate and
further refine these results. Still – I am hopeful that knowledge
of these proteins will provide guidance for future therapeutic
interventions. For instance, if we could enhance wound healing while
simultaneously decreasing inflammatory response and complement
activation, we might be able to make anti-PD-1 therapy more
effective. However, the current test as is - cause remember, these
samples were taken BEFORE any of these ratties got any anti-PD-1
therapy - could refine prediction of who would benefit from current
anti-PD-1 treatment and who may not. For instance, if your blood samples showed proteins indicating that you were likely to respond to anti-PD-1 alone, especially if we were to examine that same blood draw for circulating tumor DNA and other biomarkers, it may help your decision making process when considering anti-PD-1 therapy vs the ipi/nivo combo with its increased rate of potential side effects.
Come on, researchers. Let's get these tests out there!!! Here's to the ratties! love, c
Saturday, March 26, 2016
Biomarkers - blood components, circulating tumor cells AND of the tumor itself
Biomarkers. Sounds important. What are they? What can they really tell us?
 Researchers
have been seeking to find a connection between nonspecific biomarkers
(things we ALL have circulating in our blood) like LDH, various white
blood cells (neutrophils and monocytes - whether as an absolute count or
as a neutrophil to lymphocyte ratio), myeloid-derived suppressor cells
(MDSCs) and T-regs (See post with links about all that here: Blood markers associated with clinical outcomes). And
while many meaningful correlations have been drawn between these
components and response to treatment (or lack thereof); the fact that
they are all affected by numerous circumstances other than melanoma and
its treatment, create limitations in the clarity with which they can be
used to PREDICT responses.
With recent scientific advances, PCR testing (Polymerase chain reaction) has become more efficient and cost-effective, allowing labs to copy or "amplify" small segments of DNA or RNA though screening blood or other biological specimens. This ability allows the cellular identification of whatever may be floating in that blood sample....whether it is a virus or fungus, or actual bits and pieces of tumor cells themselves, to allow a determination of disease burden, prognosis, and response to treatment. Here is an earlier post: Circulating tumor cells: how they may eventually impact melanoma diagnosis and evaluation of response
Now there are these reports:
Liquid biopsy utility for the surveillance of cutaneous malignant melanoma patients. Haung and Hoon. Mol Oncol. 2015 Dec 17.
Circulating melanoma cells as a potential biomarker to detect metastasis and evaluate prognosis. Hida, Yoneta, Wakamatsu, et al. Australas J Dermatol. 2016 Mar 1.
With recent scientific advances, PCR testing (Polymerase chain reaction) has become more efficient and cost-effective, allowing labs to copy or "amplify" small segments of DNA or RNA though screening blood or other biological specimens. This ability allows the cellular identification of whatever may be floating in that blood sample....whether it is a virus or fungus, or actual bits and pieces of tumor cells themselves, to allow a determination of disease burden, prognosis, and response to treatment. Here is an earlier post: Circulating tumor cells: how they may eventually impact melanoma diagnosis and evaluation of response
Now there are these reports:
Liquid biopsy utility for the surveillance of cutaneous malignant melanoma patients. Haung and Hoon. Mol Oncol. 2015 Dec 17.
Cutaneous
melanoma is one of the highest incident-rate cancers with increasing
prevalence in Western societies. Despite the advent of new approved
therapeutics, the 5-year overall survival rate of stage IV melanoma
patients remains below 15%. Current treatments for late stage disease
have shown higher efficacy when treated at a lower disease burden. Thus,
blood-based biomarkers capable of detecting melanoma prior to
clinically evident distant metastasis, will improve the treatment and
outcomes for melanoma patients. To that end, effective treatment of
melanoma necessitates identification of patients at risk for developing
distant metastases. Furthermore, employing blood biomarkers that monitor
cancer progression over the course of treatment is a promising solution
to post-treatment drug resistance often developed in melanoma patients.
Non-invasive blood biomarker assays allow for regular dynamic
monitoring of disease. "Liquid Biopsy" of blood, which exploits
circulating tumor cells (CTCs), cell-free circulating tumor DNA (ctDNA)
and cell-free circulating microRNA (cmiRNA), has been shown to detect
prognostic factors for relapse in AJCC stage III and stage IV melanoma
patients. Moreover, molecular characterization of CTC and analysis of
various forms of ctDNA present promising potential in development of
individualized therapy for melanoma patients. New approaches such as
massive parallel sequencing (MPS) provide a comprehensive view of the
disease progression, allowing for the selection of therapeutic options
for individual patients. With advancements of improving molecular
assays, liquid biopsy analysis as a powerful, routine clinical assay for
melanoma patients, is highly promising prospective.
|
Circulating melanoma cells as a potential biomarker to detect metastasis and evaluate prognosis. Hida, Yoneta, Wakamatsu, et al. Australas J Dermatol. 2016 Mar 1.
Then, there's the examination of the properties of the tumor sample itself. This article talks about looking at the tumor in regard to how well it is being recognized by the immune system....specifically t-cells:
Melanoma-specific MHC-II expression represents a
tumour-autonomous phenotype and predicts response to anti-PD-1/PD-L1 therapy. Johnson, Estrada, Salgado, Sosman, et al. Nat Commun.
2016 Jan 29.
Here...the tumor is being characterized by surface molecules that are correlated with prognosis:
Molecular markers to complement sentinel node status
in predicting survival in patients with high risk locally invasive melanoma. Rowe, Tang, Hughes, et al. Int J Cancer. 2016 Mar 14.
Here the tumor is being analyzed for specific genetic variations:
Genomic and Transcriptomic Features of Response to
Anti-PD-1 Therapy in Metastatic Melanoma. Hugo, Zaretsky, Sun, et al.
Cell. 2016 Mar 15.
PD-1 immune checkpoint
blockade provides significant clinical benefits for melanoma patients. We
analyzed the somatic mutanomes and transcriptomes of pretreatment melanoma
biopsies to identify factors that may influence innate sensitivity or
resistance to anti-PD-1 therapy. We find that overall high mutational loads
associate with improved survival, and tumors from responding patients are
enriched for mutations in the DNA repair gene BRCA2. Innately resistant tumors
display a transcriptional signature (referred to as the IPRES, or innate
anti-PD-1 resistance), indicating concurrent up-expression of genes involved in
the regulation of mesenchymal transition, cell adhesion, extracellular matrix
remodeling, angiogenesis, and wound healing. Notably, mitogen-activated protein
kinase (MAPK)-targeted therapy (MAPK inhibitor) induces similar signatures in
melanoma, suggesting that a non-genomic form of MAPK inhibitor resistance
mediates cross-resistance to anti-PD-1 therapy. Validation of the IPRES in
other independent tumor cohorts defines a transcriptomic subset across distinct
types of advanced cancer. These findings suggest that attenuating the
biological processes that underlie IPRES may improve anti-PD-1 response in
melanoma and other cancer types.
While none of these (other than those that are simple measures of recognized blood components) are validated and ready for daily screening of cancer patients across this country....every step is important in helping docs...eventually....determine
the best treatment options for the individual and monitor their
response to that treatment in ways that are specific, easily measured,
and less invasive and damaging to that patient. What a beautiful day that will be!!! Minimized only by the day we figure out how to avoid cancer entirely! Hey....might as well live large and dream big!!! - c
Tuesday, December 12, 2017
A simple blood draw to measure serum protein - predicts outcome for melanoma patients treated with anti-PD-1????
So this is interesting:
A Serum Protein Signature Associated with Outcome After Anti-PD1 Therapy in Metastatic Melanoma. Sznol, Sullivan, Blackmon...Ascierto...Weber. Cancer Immunol Res. 2017 Dec 5.
A mass spectrometry analysis was performed using serum from patients receiving checkpoint inhibitors to define baseline protein signatures associated with outcome in metastatic melanoma. Pre-treatment serum was obtained from a development set of 119 melanoma patients on a trial of nivolumab with or without a multi-peptide vaccine and from patients receiving pembrolizumab, nivolumab, ipilimumab, or both nivolumab and ipilimumab. Spectra were obtained using matrix assisted laser desorption/ionization time of flight mass spectrometry. These data combined with clinical data identified patients with better or worse outcomes. The test was applied to five independent patient cohorts treated with checkpoint inhibitors and its biology investigated using enrichment analyses. A signature consisting of 209 proteins or peptides was associated with progression-free and overall survival in a multivariate analysis. Test performance across validation cohorts was consistent with the development set results. A pooled analysis, stratified by set, demonstrated a significantly better overall survival for 'sensitive' relative to 'resistant' patients. The test was associated with survival in a cohort of ipilimumab-treated patients. Test classification was associated with acute phase reactant, complement and wound healing pathways. We conclude that a pre-treatment signature of proteins, defined by mass spectrometry analysis and machine learning, predicted survival in patients receiving PD-1 blocking antibodies. This signature of proteins was associated with acute phase reactants and elements of wound healing and the complement cascade. This signature merits further study to determine if it identifies patients who would benefit from PD-1 blockade.
In line with my last post....researchers keep looking for a biomarker via a simple blood draw that will predict response to a particular treatment, indicate tumor burden, note disease progression or regression, etc. Here, researchers looked at proteins in the blood of 119 "melanoma patients on a trial of nivo with or without multi-peptide vaccine and from patients [in other immunotherapy studies]".Hmmmm.....anybody know ratties who took nivo with peptide vaccines??????? C'est moi!!! Results from the 33 ratties in my Nivolumb/Opdivo trial...published! Damn!!! The places my blood has gone with nobody telling me NOTHING about it!!!!!!!!!!!!!!!!!
ANYWAY!!!!! In this report, researchers found that a certain set of proteins, found in the blood of patients with melanoma BEFORE treatment, "predicted survival in patients receiving PD-1 blocking antibodies."
This could be very important for folks making a decision about what treatment is best for them. Melanoma is not kind to those who waste time. A way to know which treatment to spend your time taking could be life saving.
Wonder what THIS rattie's proteins showed? Seriously, how is it that clinical trials use ratties and fail to inform them of the results of their OWN tests? How is this okay? WHY wouldn't you let the folks who put their lives, dollars, families, blood, protein, EVERYTHING on the line - yes, for themselves...but also for the reputations (and CV's) of researchers and facilities as well as the monetary/stock value of Big Pharma - the results determined from their literal blood, sweat and tears? Just asking! Sadly....not expecting answers. Can only hope that these results will benefit melanoma peeps in the future!!! - c
Saturday, February 17, 2018
Circulating tumor DNA to help differentiate true progression of melanoma vs pseudoprogression in patients treated with anti-PD-1
I've been yelling for some time about the need to develop, refine and put into practice valid, reliable blood assays....whether they are measuring circulating DNA, tumor cells, various other tumor makers, white blood cells, any other floating bits and bobs...in order to diagnosis melanoma, determine the most effective treatment, and recognize progression and/or effectiveness of that treatment. Here is a link to a zillion of those reports/rants: Blood assays, tumor markers, circulating DNA, you name it!!!!
In fact, the report below is a follow-up report and specific look at pseudoprogression from this study: 2017: Circulating DNA predicts response to anti-PD1
Now, there's this -
Association Between Circulating Tumor DNA and Pseudoprogression in Patients With Metastatic Melanoma Treated With Anti-Programmed Cell Death 1 Antibodies.Lee, Long, Menzies, et al. JAMA Oncol. 2018 Feb 8.
Longitudinal circulating tumor DNA (ctDNA) has been shown to predict response and survival in patients with metastatic melanoma treated with anti-programmed cell death 1 (PD-1) antibodies. Pseudoprogression, defined as radiologic finding of disease progression prior to response, has been a challenge to clinicians.
To establish whether ctDNA at baseline and up to week 12 of treatment can differentiate between the radiologic findings of pseudoprogression and true progression in patients with metastatic melanoma.
This explorative biomarker study examined circulating BRAF and NRAS mutations in a cohort of 125 patients with melanoma receiving PD-1 antibodies alone or in combination with ipilimumab between July 3, 2014, and May 24, 2016. Pseudoprogression was defined retrospectively as radiologic progression not confirmed as progressive disease at the next radiologic assessment. Plasma samples of ctDNA at baseline and while receiving treatment were taken for analysis prospectively over the first 12 weeks of treatment. Favorable ctDNA profile (undetectable ctDNA at baseline or detectable ctDNA at baseline followed by greater than 10-fold decrease) and unfavorable ctDNA profile (detectable ctDNA at baseline that remained stable or increased) were correlated with response and prognosis.
Early differentiation of pseudoprogression from true progression using longitudinal ctDNA profile.
According to guidelines by Response Evaluation Criteria in Solid Tumors (RECIST), progressive disease occurred in 29 of the 125 patients (23.2%). Of the 29 patients, 17 (59%) were 65 years or younger, 18 (62%) were men, 9 (31%) had pseudoprogression, and 20 (69%) had true progression. Of the 9 patients (7%) with confirmed pseudoprogression, all patients had a favorable ctDNA profile. At a median follow-up of 110 weeks, 7 of 9 patients (78%) were alive. All but 2 patients with true progression had an unfavorable ctDNA profile. Sensitivity of ctDNA for predicting pseudoprogression was 90% and specificity was 100%. The 1-year survival for patients with RECIST-defined progressive disease and favorable ctDNA was 82% vs 39% for unfavorable ctDNA. Overall survival was longer in patients with a partial response (54 of 125 patients [43%]) compared with patients with progressive disease and a favorable ctDNA profile (11 of 125 patients [9%]).
The results demonstrate that ctDNA profiles can accurately differentiate pseudoprogression from true progression of disease in patients with melanoma treated with PD-1 antibodies. Results of this blood test performed at regular intervals during systemic treatment reflect tumor biology and have potential as a powerful biomarker to predict long-term response and survival.
Here researchers looked at 125 melanoma patients with BRAF and NRAS mutations treated with anti-PD-1 alone or in combination with ipi between July 2014 and May 2016. They drew their blood before and during the first 12 weeks of their treatment and correlated those findings with the patient's response and prognosis. Per the RECIST scale, progressive disease occurred in 29 of the 125. 9 had pseudoprogression and 20 had real progression. "All but 2 of the patients with true progression had an unfavorable ctDNA profile. Sensitivity of ctDNA for predicting pseudoprogression was 90% and specificity was 100%." The 1 year survival for the folks with RECIST defined progression but WITH the favorable blood test ctDNA was 82%, while for folks with an unfavorable ctDNA it was only 39%. "The results demonstrate that ctDNA profiles can accurately differentiate pseudoprogression from true progression of disease in patients with melanoma treated with PD-1 antibodies."
I think we've yammered about this stuff enough. Consistent, available, defined blood assays need to be made readily available for melanoma patients!!!! C'mon man!!!! - c
Tuesday, June 14, 2011
Busy weekend...as usual!
Last Thursday, it was back to Tampa. Saw Dr. Weber on Friday. Brent had lots of questions. Weber repeated the info about my cohort in the study...saying that still...only two, early on, had had to withdraw from the study. Did find out an interesting factoid. Weber said that the FDA forced him to use Stage 4 disease patients in this study. He said it as though he had wished otherwise, because we are the group that has such a dismal prognosis no matter what you do to us. Didn't have the presence of mind to ask why the FDA did that...but anyway. He told Brent that I was in an elite group...since all of us, except the initial poor two, have remained disease free, me for 6 months and some in this study for 9. Folks in this category are lucky if they stay disease free for two months. So....for what it's worth.
Leukophoresis was rather hectic...what with waiting for over an hour before anything was started. Then, IV's were started with only one stick each, which was good, but they didn't seem to be functioning well. I do have limited vein options given what they've been through over the past 6 months, and especially in the last week. At any rate, the machine kept beeping indicating poor flow and the techs would come fiddle with things. Ended up staying on the machine for over 3 hours and had to stay stock still as the lines were so precarious. Got a terrible crick in my neck..that is still aggravating me. Also discovered another factoid. I asked about the gauge (size) of the lines they put in to collect and return the blood for the phoresis and was told that it is one size smaller than that used for blood collection at blood banks. Well...I think that is STUPID!! The pain is not appreciably less, with that slightly diminished size, but the size is too small for red blood cells to funnel through unharmed (that's why blood banks use a larger size...no need to collect and give damaged cells to patients). NO WONDER I GET ANEMIC AND FEEL SO TIRED after. They go to all the trouble to give me back most of the red blood cells but they are so buggered up that they don't do me that much good. What's the deal with that?!!!! Anyway...the whole deal took so long that it was a bit of a rush to get to the airport in time for our flight. Had to be felt up once again, for good measure, by the wonderful gals in the TSA in Tampa! Good grief!
Anyway....got to spend some good time with the Roo. We picked her up on our return to Atlanta and brought her home with us for some R&R. I took her back to Tech on Sunday afternoon. She's a real cutie. Miss her already!! Work's been fine, but busy.....and tomorrow Brent and I will be returning to Atlanta when I get off work for some meetings he has and some relaxing and some visiting with Rosie. Looking forward to the gardens, maybe the art museum, and DeKalb. We'll see...just gonna chill and return home on Sunday.
Here's to plump RBC's!!!!! - c
FYI - Ipilimumab is now approved and on the market under the brand name of Yervoy. Don't ask. I don't know where they get these names. It's yours for the bargain basement price of a really dreadful diagnosis and $30,000.00 per dose. Treatment requires 4 doses!!! And, my anti-PD1 infusion also goes by the name of MDX1106....so don't let all this confuse you if you see stuff being reported from ASCO (annual oncology conference) that was just held in Chicago. c
Saturday, February 24, 2018
More blood tests to determine prognosis as well as response to therapy in melanoma patients!!!
It is becoming more and more clear (at least to me!!!!!!!!!) that there are all sorts of ways of looking at blood markers in order to diagnose, predict progression and response, as well as evaluate response to a particular treatment in melanoma patients. Here is my latest post with a zillion links within: Circulating tumor DNA to help differentiate true progression of melanoma vs pseudoprogression in patients treated with anti-PD-1 Now, there's this ~
Performance of a prognostic 31-gene expression profile in an independent cohort of 523 cutaneous melanoma patients. Zager, Gastman, Leachman, et al. BMC Cancer. 2018 Feb 5.
The heterogeneous behavior of patients with melanoma makes prognostication challenging. To address this, a gene expression profile (GEP) test to predict metastatic risk was previously developed. This study evaluates the GEP's prognostic accuracy in an independent cohort of cutaneous melanoma patients.
This multi-center study analyzed primary melanoma tumors from 523 patients, using the GEP to classify patients as Class 1 (low risk) and Class 2 (high risk). Molecular classification was correlated to clinical outcome and assessed along with AJCC v7 staging criteria. Primary endpoints were recurrence-free (RFS) and distant metastasis-free (DMFS) survival.
The 5-year RFS rates for Class 1 and Class 2 were 88% and 52%, respectively, and DMFS rates were 93% versus 60%, respectively. The GEP was a significant predictor of RFS and DMFS in univariate analysis , along with Breslow thickness, ulceration, mitotic rate, and sentinel lymph node (SLN) status . GEP, tumor thickness and SLN status were significant predictors of RFS and DMFS in a multivariate model that also included ulceration and mitotic rate .
The GEP test is an objective predictor of metastatic risk and provides additional independent prognostic information to traditional staging to help estimate an individual's risk for recurrence. The assay identified 70% of stage I and II patients who ultimately developed distant metastasis. Its role in consideration of patients for adjuvant therapy should be examined prospectively.
Think how great this sort of information would be when trying to determine whether or not to utilize adjuvant therapy!!!
But, that's not all! There's also this ~
Molecular signatures of circulating melanoma cells for monitoring early response to immune checkpoint therapy. Hong, Sullivan, Kalinich, et al. Proc Natl Acad Sci U S A. 2018 Feb 16.
A subset of patients with metastatic melanoma have sustained remissions following treatment with immune checkpoint inhibitors. However, analyses of pretreatment tumor biopsies for markers predictive of response, including PD-1 ligand (PD-L1) expression and mutational burden, are insufficiently precise to guide treatment selection, and clinical radiographic evidence of response on therapy may be delayed, leading to some patients receiving potentially ineffective but toxic therapy. Here, we developed a molecular signature of melanoma circulating tumor cells (CTCs) to quantify early tumor response using blood-based monitoring. A quantitative 19-gene digital RNA signature (CTC score) applied to microfluidically enriched CTCs robustly distinguishes melanoma cells, within a background of blood cells in reconstituted and in patient-derived (n = 42) blood specimens. In a prospective cohort of 49 patients treated with immune checkpoint inhibitors, a decrease in CTC score within 7 weeks of therapy correlates with marked improvement in progression-free survival and overall survival. Thus, digital quantitation of melanoma CTC-derived transcripts enables serial noninvasive monitoring of tumor burden, supporting the rational application of immune checkpoint inhibition therapies.
Blood draws with more detailed info than repeated radiological studies!!! C'mon man!!! Let's get some consensus and make these tests available for patients in need! - c
Saturday, February 29, 2020
Circulating tumor DNA in melanoma - Yep. AGAIN!!!
If you've hung around this space for half a minute, you know that I've long been yelling about "liquid assays" (including ctDNA) that can diagnose, predict, and evaluate progression or response in melanoma patients. Perhaps more importantly, despite the clear benefit of these tests, they remain pretty much unavailable to most melanoma patients. Here are only a zillion reports: Melanoma and circulating tumor DNA
Now there are these:
Prediction and monitoring of relapse in stage III melanoma using circulating tumor DNA. Tan, Sandhu, Lee, et al. Ann Oncol. 2019 May 30.
The advent of effective adjuvant therapies for patients with resected melanoma has highlighted the need to stratify patients based on risk of relapse given the cost and toxicities associated with treatment. Here we assessed circulating tumor DNA (ctDNA) to predict and monitor relapse in resected stage III melanoma.
Somatic mutations were identified in 99/133 (74%) patients through tumor tissue sequencing. Personalized droplet digital PCR (ddPCR) assays were used to detect known mutations in 315 prospectively collected plasma samples from mutation-positive patients. External validation was performed in a prospective independent cohort (n=29).
ctDNA was detected in 37 of 99 (37%) individuals. In 81 patients who did not receive adjuvant therapy, 90% of patients with ctDNA detected at baseline and 100% of patients with ctDNA detected at the postoperative time point relapsed at a median follow up of 20 months. ctDNA detection predicted patients at high risk of relapse at baseline and postoperatively. ctDNA detection at baseline and postoperatively was also associated with inferior distant metastasis-free survival (DMFS). These findings were validated in the independent cohort. ctDNA detection remained an independent predictor of RFS and DMFS in multivariate analyses after adjustment for disease stage and BRAF mutation status. Baseline and postoperative ctDNA detection in two independent prospective cohorts identified stage III melanoma patients at highest risk of relapse and has potential to inform adjuvant therapy decisions.
ctDNA was detected in 37 of 99 (37%) individuals. In 81 patients who did not receive adjuvant therapy, 90% of patients with ctDNA detected at baseline and 100% of patients with ctDNA detected at the postoperative time point relapsed at a median follow up of 20 months. ctDNA detection predicted patients at high risk of relapse at baseline and postoperatively. ctDNA detection at baseline and postoperatively was also associated with inferior distant metastasis-free survival (DMFS). These findings were validated in the independent cohort. ctDNA detection remained an independent predictor of RFS and DMFS in multivariate analyses after adjustment for disease stage and BRAF mutation status. Baseline and postoperative ctDNA detection in two independent prospective cohorts identified stage III melanoma patients at highest risk of relapse and has potential to inform adjuvant therapy decisions.
|
Circulating tumor cells and early relapse in node-positive melanoma. Lucci, Hall, Patel, et al. Clin Cancer Res. 2020 Feb 3.
There is a need for sensitive, reproducible biomarkers for stage III melanoma patients to guide clinical decision making. Circulating tumor cells (CTCs) can be detected in melanoma patients; however, there is limited data regarding their significance in stage III disease. The aim of this study was to determine if CTCs are associated with early relapse in stage III melanoma.
We prospectively assessed CTCs at first presentation in clinic (baseline) for 243 stage III melanoma patients. CTCs were measured using the CellSearch System. Relapse-free survival (RFS) was compared between patients with one or more baseline CTC versus those with no CTCs. Log-rank test and Cox regression analysis were applied to establish associations of CTCs with RFS. At least one baseline CTC was identified in 90/243 (37%) patients. Forty-five (19%), 67 (28%), 118 (49%), and 13 (5%) patients were stage IIIA, IIIB, IIIC, or IIID, respectively. CTC detection was not associated with sub stage, or primary tumor characteristics. Multivariable analysis demonstrated that the detection of greater than/= to 1 baseline CTC was significantly associated with decreased 6 month RFS and 54 month RFS. Greater than/= to 1 CTC was independently associated with melanoma relapse, suggesting that CTC assessment may be useful to identify patients at risk for relapse who could derive benefit from adjuvant therapy. |
Circulating tumour cells (CTCs) are cells of solid tumour origin detectable in the peripheral blood. Their occurrence is considered a prerequisite step for establishing distant metastases. Metastatic melanoma was the first malignancy in which CTCs were detected and numerous studies have been published on CTC detection in melanoma at various stages of disease. In spite of this, there is no general consensus as to the clinical utility of CTCs in melanoma, largely due to conflicting results from heterogeneous studies and discrepancies in methods of detection between studies. In this review, we examine the possible clinical significance of CTCs in cutaneous, mucosal and ocular melanoma, focusing on detection methods and prognostic value of CTC detection.
Despite very convincing data and a desperate need in the patient population these tests remain unavailable to the average patient. Will the desire of firms to make a buck, make a difference?
This report from CNBC tech, 2/2020 : These start-ups are racing to help doctors detect cancer early with a simple blood test
Which states, in part: "Getting a blood test to screen for cancer in the earliest stages might seem like a pipe dream. But a group of biotech entrepreneurs say they’re close to making it a reality. If Gabriel Otte’s start-up, Freenome, is successful, millions of people could get a blood test to screen for early-stage colorectal cancer. Freenome looks for two major biomarkers in the blood. It’s simultaneously hunting for tiny fragments of DNA that are shed into the bloodstream from a tumor, as well as early signals that the patient’s immune system is starting to respond. The medical industry has known for years that that blood-based “liquid biopsies” can find signatures of cancer. But the tests on the market today focus on monitoring the progression of the disease once a patient has been diagnosed with cancer, including how it’s responding to treatment. The next generation of companies want to detect cancer while it’s early and often easier to treat."
We know these tests work. We know they could provide a great deal of helpful information for melanoma patients facing hard choices. It is past time that they be made available. For what it's worth. ~ c
Subscribe to:
Posts (Atom)